
Written by Doug Wallace
Spoon Feed
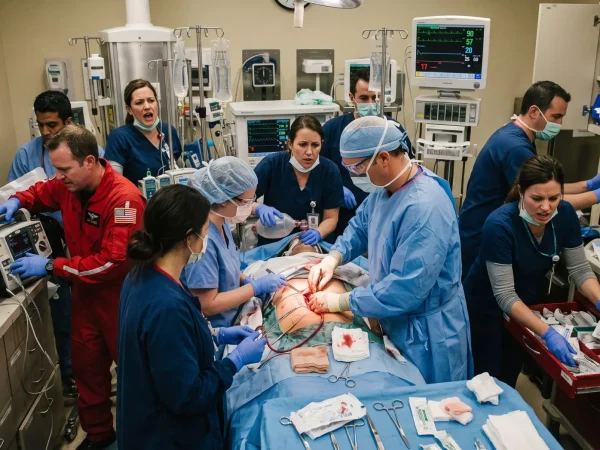
Emergency thoracotomy has evolved with our specialty. This practical review provides an updated approach to indications, technique, and post-thoracotomy management, with a focus on getting the chest open efficiently and safely.
Cracking the chest
This review updates the classic 2005 “how-to” for emergency thoracotomy (ET), incorporating newer guidelines and operational experience. The authors recommend considering ET within 15 minutes of loss of vital signs, while emphasizing mechanism, signs of life, and suspected pathology.
The clamshell to maximize exposure remains the preferred method. The authors recommend a stepwise approach:
- Position the arms in a crucifix position.
- Make bilateral anterolateral thoracotomy incisions and divide the sternum to create the “clamshell”.
- Open the pericardium longitudinally, avoiding the phrenic nerve, and evacuate tamponade.
- Control cardiac wounds with direct pressure and, when needed, sutures. Avoid the old-school teaching of using a foley.
- Control pulmonary hemorrhage with pressure, non-crushing clamps, or hilar twist as a last resort.
- Release the inferior pulmonary ligament when needed to mobilize the lung and improve access to the descending aorta.
- Compress the descending thoracic aorta against the vertebral column, progressing to clamping when appropriate. Make sure not to clamp the esophagus (can use an NG to identify).
- Begin two-handed internal cardiac massage at 80–100 compressions/minute. Defibrillate / administer epi (preferably not intracardiac) when needed.
- Control any other outstanding hemorrhage (and give blood).

The authors also emphasize the importance of team roles, checklists, simulation, and what to do if you actually get ROSC for this high-acuity, low-frequency procedure.
How will this change my practice?
ED thoracotomy is a true high-acuity, low-frequency procedure with little room for hesitation when indicated. This review is a great refresher on the approach, but more importantly, a reminder to rehearse the procedure with your team and know your equipment before you actually need it.
Editor’s note: The guidelines imply that the <15 minute cutoff is primarily for cases of cardiac tamponade. For exsanguination-induced cardiac arrest, after >5 minutes ED thoracotomy may be futile. ~Nick Zelt
Source
Emergency thoracotomy: how to do it in 2026 . Emerg Med J. 2026 Aug 24:emermed-2026-216110. doi: 10.1136/emermed-2026-216110. Epub ahead of print. PMID: 42637522.